I have published over 400 peer-reviewed papers. I now work directly with practising clinicians on their first one. Most of the time people lose is not spent writing; it is spent on a topic that was never going to work.
Apply to work with meTwo minutes. Every application gets a reply.
Start here · about 30 minutes
Choosing a topic that can actually be answered, using the Convergence Method. Running a Forensic Search that gives you an argument instead of nine hundred PDFs. Writing in the order that does not stall. Watch this first; the application will make more sense afterwards.
Who you would be working with
I was a full professor at Oxford in my early thirties and a tenure-track professor at Harvard. My PhD is from Cambridge. I have published over 400 peer-reviewed papers, in journals including Nature, The Lancet, the British Medical Journal, PLoS Medicine and PNAS.
What interests me now is a structural problem: why so many capable clinicians never publish. Universities assume you will absorb the mechanics by osmosis. Supervisors are stretched thin. Careful people lose years on topics that were doomed from the first week. FastTrack is what I wish someone had taught me at the beginning.
Why it takes people so long
Most first papers are lost here, months before anyone writes a sentence. The question is unanswerable with the data available, or it has been answered four times already.
An unfocused literature search returns nine hundred papers and no argument. Done properly it returns forty and tells you exactly where your contribution sits.
People write the introduction first. It is the last thing you can write honestly, and starting there is why drafts stall at 60 percent for a year.
Fix those three and the timeline collapses, not because anyone worked faster, but because the wasted year never happens. That is the whole of what I teach.
AI / Why not just use AI?
AI is good at the next sentence. It's bad at the next six months. It will polish a literature review for a topic that was never publishable, agree with a framing a reviewer will reject, and send you confidently down dead-ends, because it optimises for the answer in front of it, not for your career. What gets clinicians published isn't more information. It's judgement: knowing which topic survives peer review, when a draft is done, and when to stop reading and start writing. That's what the mentorship gives you.
Our commitment
Five to ten hours a week, around clinical work. The method's job is to make sure none of those hours are spent on a dead end.
That holds as long as you hold up your end:
That's the whole arrangement. No small print about which journals count, and no time limit that ends your support.
The timeline
First weeks: protocol pre-registered · Months 0–3: write and submit · 2–4 months: peer review · Revisions · Acceptance typically 9–12 months
Your CV moves first: for systematic reviews and trial studies we pre-register your protocol in the opening weeks, which puts a citable research line on your CV almost immediately. Most researchers submit at the three-month mark. Peer review typically takes two to four months, then revisions, which are normal rather than a sign something went wrong. Acceptance typically lands nine to twelve months from the start. Our commitment sits underneath all of it: if your paper takes longer, we stay, at no extra cost.
Where most clinicians start
Many of the clinicians we work with publish a systematic review first. It is what your clinical guidelines are built on, it sits at the top of the evidence hierarchy, and it runs entirely on published literature. No data collection, no ethics committee, nothing that cannot be done in five to ten hours a week around clinical work. Our systematic review programme takes you through it step by step, from question to submission.
In their own words
Hospice and palliative medicine physician, six years in practice. Published in a peer-reviewed journal in her specialty. She had a baby partway through.
Physician with a military background and no first-author experience. Published three papers, including a systematic review, and was admitted with funding to doctoral programmes at Johns Hopkins, Berkeley and Boston University.
Published her first systematic review and a bioinformatics paper. Joined without a topic; it came out of her roadmap session.
Evidence
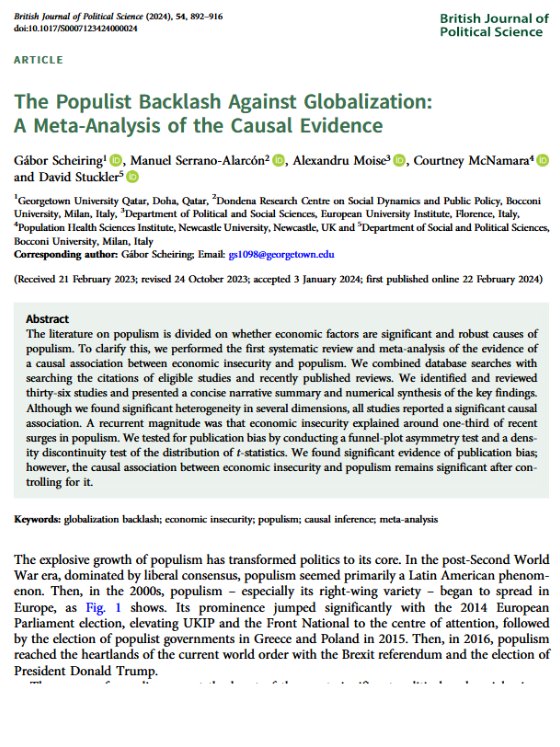
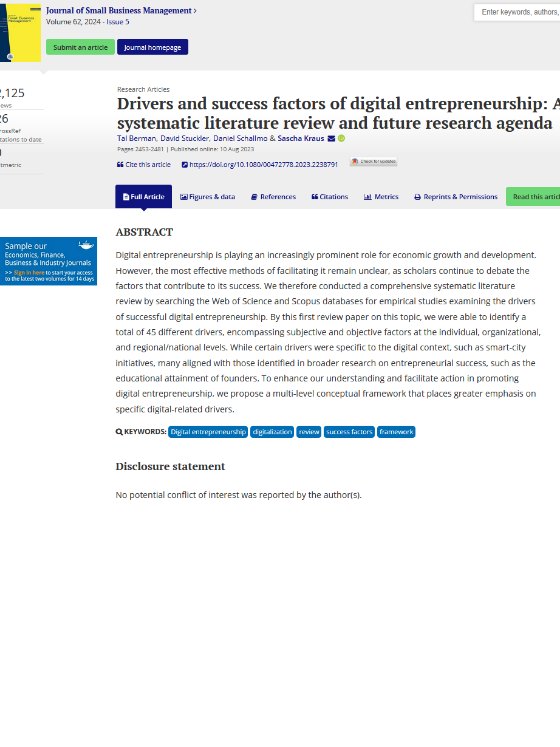
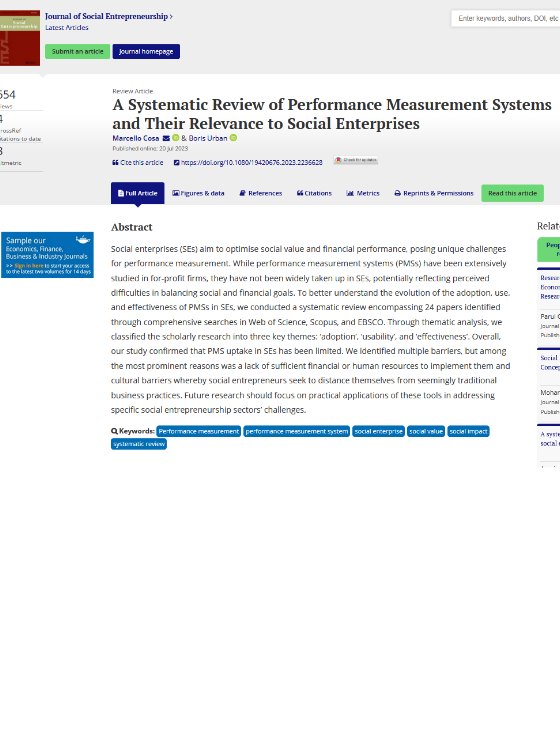
Named authors. Real journals. Most link straight to the paper.


What you get
Asked and answered
Most people start there, and it's the best place to start, because the topic is where first papers are won or lost. In your roadmap session we generate and validate topic ideas against your interests, your access to data and your hours, using the Convergence Method, and map out three or four viable research questions. You leave with a validated topic, and you learn the method, so you can do it yourself for every paper after.
Most researchers submit at three months. Peer review typically takes two to four months, then revisions, with acceptance typically nine to twelve months in. For systematic reviews and trials, your protocol is pre-registered and citable within the first few weeks. I do not put a date on acceptance, because that date is not mine to set, but if it runs longer, I am still with you. Most researchers work five to ten hours a week. If a stretch of rota makes that impossible, we adapt the plan; consistency matters more than intensity.
Much more than a course. You get a roadmap session that turns where you are now into a step-by-step plan, unlimited direct messaging with Prof Stuckler and the mentor team, two live group feedback workshops a week, detailed video feedback on everything you submit, and a community for day-to-day help. We guide you through execution; we don't hand you videos and wish you luck.
The videos teach the method. The mentorship applies it to your paper. The difference is feedback on your actual work: your topic validated against the literature, your drafts marked up, your next step always clear. Watching someone else's paper get fixed is not the same as having yours fixed.
Submit your work at any stage: research questions, abstracts, literature reviews, draft sections. You get detailed video feedback, often screen-recorded with commentary, showing exactly what to change. There's live feedback at the weekly workshops, and if your rota means you miss them, you still submit and still get a personalised video response.
Almost certainly. The methods apply across clinical medicine, surgery, nursing, public health, psychiatry, global health and health policy. The frameworks for choosing a topic, running a clean literature review, writing methods and getting through peer review do not change between specialties. The one honest exception: if you need advanced technical support on bench science or bioinformatics pipelines, we are not the right place. We can usually point you to someone in our network who is.
No. We work alongside them, not around them. Most people join because the person nominally supervising them is stretched across a full clinical service, not because nobody is there. Many find those conversations get more productive once they arrive with a validated question and a structured draft.
No, and many of the people listed above started there. What you need is consistent weekly hours. You do not need a methods background. That is the part I teach.
Yes. Your work stays between you and the mentor team, and your ideas remain yours. We agree any authorship openly at the roadmap session, and only if you want it and the contribution earns it.
Only if you want that, and only where the contribution meets authorship criteria. Some researchers invite a mentor onto the paper; others keep sole authorship. The support is identical either way, and we agree it openly at the roadmap session rather than at the end.
Yes. Study design, data collection and analysis, with support for R, Stata and SPSS.
That is what the commitment is for. If you are still putting in the hours, I am still working with you, past the three months, at no extra cost.

Apply
The next step is a thirty-minute strategy call. We use it to find the single biggest thing slowing your research down, and to build a plan for your next publication. I work with clinicians who can commit five to ten hours a week over three months.
Direct mentorship starts at $3,000 over three months. The application takes two minutes, and we'll point you to the right path either way.
Apply to work with me